What Is Srs Surgery Explained Clearly Today
Gender-affirming surgeries have evolved from controversial medical experiments into life-saving procedures, offering transgender and non-binary individuals a path toward alignment between identity and body. At the core of this transformation lies SRS—Sex Reassignment Surgery—a term increasingly replaced by Gender Affirming Surgery (GAS) and Gender Confirmation Surgery (GCS) as medical understanding and societal acceptance advance. For many, these surgeries represent more than physical change; they symbolize liberation, self-determination, and the right to live authentically in a world often resistant to diversity.
Yet behind the growing accessibility of GAS lies a complex web of medical science, psychological evaluation, and legal hurdles that vary drastically across regions. From the first recorded gender reassignment in the early 1900s to today’s minimally invasive techniques, the journey reflects both medical progress and the persistent struggle for transgender rights. This guide unpacks the history, procedures, and prerequisites of SRS, debunking myths while illuminating the realities faced by those seeking gender-affirming care—a process that demands not just surgical expertise, but also compassionate mental health support and systemic change.

Understanding Sex Reassignment Surgery: Core Concepts, Historical Evolution, and Modern Terminology

Sex Reassignment Surgery (SRS) represents a pivotal medical intervention for individuals seeking alignment between their gender identity and physical characteristics. Over time, the terminology surrounding these procedures has evolved to reflect broader understandings of gender diversity, shifting from SRS to more inclusive terms like Gender Affirming Surgery (GAS) and Gender Confirmation Surgery (GCS). This transformation mirrors advancements in medical ethics, legal recognition, and societal acceptance of transgender and non-binary identities. While SRS historically emphasized binary gender transitions, modern frameworks now encompass a spectrum of identities, including those outside the male-female binary, and prioritize affirming care over rigid medical classifications.
The distinction between these terms is not merely semantic but reflects shifts in medical practice, patient autonomy, and cultural sensitivity. Legal and regional variations further complicate the landscape, with countries adopting different terminologies based on healthcare policies, cultural norms, and historical contexts. For example, the U.S. often uses GAS, while Europe may lean toward GCS, and Asia varies widely depending on local medical traditions and legal frameworks. Understanding these nuances is essential for patients, healthcare providers, and policymakers to navigate the complexities of gender-affirming care.
Definitions and Terminological Shifts in Gender-Affirming Surgery
The terminology surrounding gender-affirming procedures has undergone significant refinement to better reflect the diversity of gender identities and reduce stigma. Below is a comparison of key terms, their definitions, and their common usage in medical and legal contexts:
| Term | Definition | Common Usage |
|---|---|---|
| Sex Reassignment Surgery (SRS) | A historical term referring to surgical interventions aimed at altering primary or secondary sexual characteristics to align with a person’s gender identity. Often associated with binary transitions (male-to-female or female-to-male) and rooted in early 20th-century medical practices. | Still used in some regions, particularly in older medical literature or legal documents. Considered outdated in progressive healthcare settings due to its binary and pathologizing connotations. |
| Gender Affirming Surgery (GAS) | A contemporary term emphasizing the affirmation of a person’s gender identity through surgical or non-surgical interventions. Encompasses a broader range of procedures, including those for transgender, non-binary, and gender-nonconforming individuals. | Widely adopted in the U.S., Canada, and other regions with progressive gender healthcare policies. Preferred by medical organizations like the World Professional Association for Transgender Health (WPATH) and American Medical Association (AMA). |
| Gender Confirmation Surgery (GCS) | A term emphasizing the confirmation of a person’s gender identity through medical interventions, often used in regions where "affirmation" may carry additional connotations (e.g., legal or social). Focuses on the medical validation of gender identity rather than reassignment. | Common in Europe, Australia, and some Asian countries. Reflects a more neutral or procedural approach, aligning with healthcare systems that prioritize medical accuracy over identity-affirming language. |
The shift from SRS to GAS or GCS underscores a broader movement toward patient-centered care, where terminology is chosen to minimize harm and align with individual experiences. For instance, GAS is often preferred by transgender advocates because it avoids framing surgery as a "reassignment" (implying a correction of a perceived error) and instead positions it as an affirmative act of self-determination. Meanwhile, GCS may be favored in regions where legal systems require precise medical documentation to recognize gender transitions.
Table of Contents
- Understanding Sex Reassignment Surgery: Core Concepts, Historical Evolution, and Modern Terminology
- Definitions and Terminological Shifts in Gender-Affirming Surgery
- Historical Context: The Evolution of Gender Reassignment Surgery
- Legal and Medical Distinctions Medical and Surgical Procedures in Sex Reassignment Surgery (SRS) Sex reassignment surgery (SRS), now more commonly referred to as gender-affirming surgery (GAS), encompasses a range of specialized medical procedures designed to align a person’s physical anatomy with their gender identity. These interventions are tailored to individual needs, whether feminizing, masculinizing, or exploring non-binary or alternative gender expressions. The procedures involve precise surgical techniques, multidisciplinary collaboration, and adherence to ethical and medical guidelines, such as those established by the World Professional Association for Transgender Health (WPATH). Understanding the types of surgeries, their processes, and the roles of hormone therapy (HRT) is critical for individuals seeking gender affirmation, as well as for healthcare providers ensuring evidence-based care. Primary Types of Gender-Affirming Surgical Procedures
- Detailed Surgical Process: Vaginoplasty
- Comparison of Phalloplasty and Metoidioplasty
- Pre-SRS Preparation – Psychological, Legal, and Physical Requirements
- Psychological Evaluation Process and Diagnostic Criteria
- Legal Documentation Checklist for SRS Approval
- Physical Preparation for SRS: HRT Stabilization and Medical Optimization
- Step-by-Step Pre-Surgery Approval Process
Historical Context: The Evolution of Gender Reassignment Surgery
The history of gender reassignment surgery is a narrative of medical innovation, ethical debates, and societal progress. Early attempts to surgically alter sex characteristics emerged in the late 19th and early 20th centuries, driven by both scientific curiosity and the growing recognition of gender diversity. Below is a timeline highlighting key milestones in the development of SRS/GAS/GCS:
| Year | Significant Event |
|---|---|
| 1869 | First recorded sex reassignment attempt: Hungarian physician Dr. Richard von Krafft-Ebing documented cases of individuals seeking surgical interventions to alter their physical sex, though these were not yet standardized procedures. |
| 1917 | First documented orchiectomy for gender transition: German sexologist Magnus Hirschfeld performed the first recorded removal of testicles for a transgender man, marking one of the earliest medical interventions for gender dysphoria. |
| 1931 | First vaginoplasty: German surgeon Dr. Ludwig Levy-Lenz performed the first surgical creation of a vagina for a transgender woman, using skin grafts from the forearm. |
| 1952 | First phalloplasty: Swedish surgeon Dr. George J. Beech performed the first penile construction surgery for a transgender man, though early techniques were rudimentary and carried high risks. |
| 1966 | First successful gender reassignment surgery with hormone therapy: Danish endocrinologist Dr. Christian Hamburger and surgeon Dr. Georgio Bertini performed the first combined hormone therapy and surgical procedure for a transgender woman, Lili Elbe, though she passed away shortly after complications. |
| 1979 | WPATH founded: The Harry Benjamin International Gender Dysphoria Association (HBIGDA), later renamed World Professional Association for Transgender Health (WPATH), was established to set medical standards for gender-affirming care, including surgery. |
| 1990s | Advancements in surgical techniques: Introduction of radial forearm free flap vaginoplasty (a more reliable method for vaginal construction) and improved phalloplasty techniques using forearm or thigh tissue. |
| 2000s | Shift toward gender-affirming care: Medical guidelines began emphasizing informed consent models, reducing mandatory psychological evaluations and prioritizing patient autonomy. The term Gender Affirming Surgery (GAS) gained traction in progressive healthcare settings. |
| 2010s–Present | Minimally invasive and non-surgical options: Advances in hormone therapy, laser hair removal, fat transfer techniques, and gender-affirming voice training expanded the scope of care beyond surgery. Legal recognition of gender transitions (e.g., U.S. Supreme Court’s Bostock v. Clayton County (2020)) further normalized access to gender-affirming procedures. |
The early 20th century was marked by experimental and often risky procedures, with high rates of complications and limited medical support. The mid-20th century saw the emergence of structured protocols, particularly through the work of Dr. Harry Benjamin, a pioneer in transgender healthcare who advocated for comprehensive gender-affirming care. By the 1970s and 1980s, surgical techniques improved significantly, though access remained limited due to stigma, legal barriers, and lack of insurance coverage.
The 21st century has witnessed a paradigm shift toward patient-led care, with organizations like WPATH advocating for informed consent models—where individuals can access gender-affirming surgeries without mandatory psychiatric evaluations, provided they meet basic health criteria. This approach aligns with research showing that gender-affirming care reduces rates of depression, suicide, and gender dysphoria among transgender and non-binary individuals.
Legal and Medical Distinctions
Medical and Surgical Procedures in Sex Reassignment Surgery (SRS)
Sex reassignment surgery (SRS), now more commonly referred to as gender-affirming surgery (GAS), encompasses a range of specialized medical procedures designed to align a person’s physical anatomy with their gender identity. These interventions are tailored to individual needs, whether feminizing, masculinizing, or exploring non-binary or alternative gender expressions. The procedures involve precise surgical techniques, multidisciplinary collaboration, and adherence to ethical and medical guidelines, such as those established by the World Professional Association for Transgender Health (WPATH). Understanding the types of surgeries, their processes, and the roles of hormone therapy (HRT) is critical for individuals seeking gender affirmation, as well as for healthcare providers ensuring evidence-based care.
Primary Types of Gender-Affirming Surgical Procedures
Gender-affirming surgeries are categorized based on the desired anatomical changes, with each procedure addressing specific goals related to genital, chest, facial, or reproductive anatomy. Below are the three primary categories of surgeries, each with distinct techniques and considerations.
Feminizing surgeries focus on creating secondary female sex characteristics, including breast development, genital reconstruction, and facial feminization. These procedures are often pursued by transgender women (assigned male at birth) and some non-binary individuals seeking feminization. Key examples include:
Detailed Surgical Process: Vaginoplasty
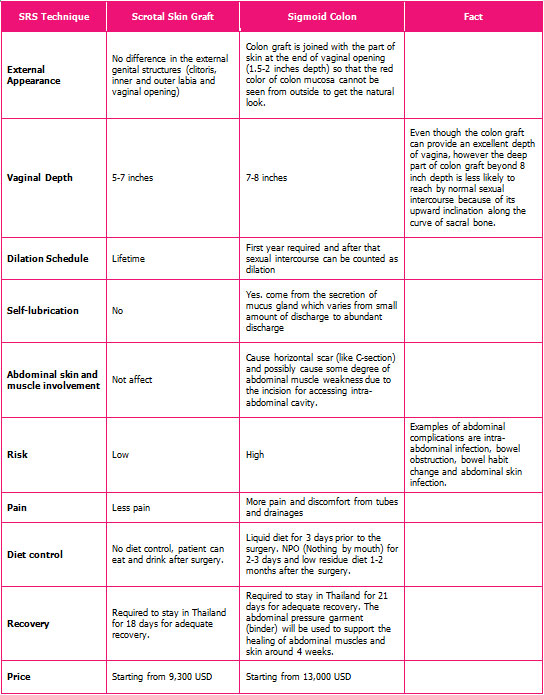
Vaginoplasty is one of the most common feminizing gender-affirming surgeries, involving the creation of a vaginal canal, vulva, and clitoris using existing penile and scrotal tissue. The procedure is typically performed under general anesthesia and requires 2–4 hours, though complexity may vary. Below is a step-by-step breakdown of the process, including anatomical transformations: 1. Preoperative PreparationComparison of Phalloplasty and Metoidioplasty
Both phalloplasty and metoidioplasty are masculinizing procedures aimed at constructing a penis-like structure, but they differ significantly in technique, recovery, and outcomes. Below is a comparative analysis presented in a structured table:| Procedure | Recovery Time | Sensate Outcomes | Eligibility Criteria | ||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Phalloplasty Construction of a neophallus using tissue grafts (radial forearm, anterolateral thigh, or other donor sites). Includes urethral lengthening and scrotoplasty. |
6–12 months for full recovery, including multiple stages:
|
Partial to full sensation depends on the donor site and nerve anastomosis (surgical reconnection of nerves).
Pre-SRS Preparation – Psychological, Legal, and Physical RequirementsThe journey toward sex reassignment surgery (SRS) begins long before the operating room, demanding meticulous preparation across psychological, legal, and physical domains. This phase ensures patients are emotionally stable, legally compliant, and medically optimized for surgery. Each step—from rigorous mental health evaluations to securing legal documentation and stabilizing physical health—serves as a critical safeguard against complications and regret. The process varies by region but adheres to ethical and medical standards to prioritize patient well-being and informed decision-making.Psychological Evaluation Process and Diagnostic CriteriaPsychological readiness is the cornerstone of SRS eligibility, requiring adherence to standardized diagnostic frameworks and therapeutic milestones. The Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) classifies gender dysphoria (previously gender identity disorder) as the primary diagnostic criterion, defined by persistent distress arising from a mismatch between one’s assigned sex and gender identity. However, not all clinicians follow DSM-5 strictly; some adopt the World Professional Association for Transgender Health (WPATH) Standards of Care (SOC), which emphasize lived experience over rigid diagnostic labels. Therapy typically spans 12–24 months, involving regular sessions with a gender specialist to explore identity, mental health, and social transition readiness. Key foci include:"My therapist asked me to reflect on how I felt after a year of living as my true self—not just the excitement of transitioning, but the exhaustion of hiding for decades. The RLE wasn’t just a checklist; it was proof I wasn’t running from something, but toward a life I deserved." — Alex, non-binary patient, pre-SRS evaluation (2021) Legal Documentation Checklist for SRS ApprovalLegal preparation ensures patients meet institutional and governmental requirements, which can differ significantly by country. Below is a standardized checklist of documents commonly requested by surgeons, insurers, or legal authorities:
"The court process in my state was the most stressful part. I had to prove my gender identity to a judge who’d never met me—while also explaining why my birth certificate needed to change. The paperwork alone took six months, and the fees for legal name changes added up fast." — Mia, transgender woman, pre-SRS (2023) Physical Preparation for SRS: HRT Stabilization and Medical OptimizationPhysical readiness minimizes surgical risks and optimizes outcomes. Hormone replacement therapy (HRT) must stabilize for 12+ months before SRS to:"I had to stop smoking cold turkey—my surgeon said even one cigarette could ruin my results. The cravings were brutal, but seeing my skin heal better post-op made it worth it. Also, my doctor made me promise to hit the gym; I needed to lose 20 pounds before my vaginoplasty." — Jamie, transgender man, pre-op (2022) Step-by-Step Pre-Surgery Approval ProcessThe approval pathway varies by clinic but generally follows a structured sequence involving multiple stakeholders. Below is a standardized table outlining the process:
|
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Verypet.